Jinkushal Cardiac Care & Superspeciality hospital


AI & Intravascular Imaging (IVUS/OCT)
How Modern Angioplasty Replaced “Blind” Stenting ?
The future of Angioplasty isn’t just about placing a stent. It’s about knowing exactly where, why, and how that stent should be placed.
Imagine trying to repair a pipe by looking only at its outer outline.
You can see where the pipe appears narrow—but you cannot see everything happening inside it.
For decades, coronary angioplasty largely depended on Angiography—a specialised X-ray technique that allows cardiologists to see the coronary arteries and identify significant narrowings.
Angiography remains an essential part of coronary intervention.
But modern interventional cardiology has gone a step further.
Today, technologies such as IVUS (Intravascular Ultrasound), OCT (Optical Coherence Tomography), and Artificial Intelligence (AI) are helping cardiologists look deeper, measure more precisely and make more informed decisions during angioplasty.
This is the evolution of Percutaneous Coronary Intervention (PCI), commonly known as coronary angioplasty
From seeing the artery → to seeing inside the artery → to using advanced technology to guide treatment.
Why Angiography Alone May Not Tell the Whole Story?
During conventional coronary angiography, contrast dye is injected into the coronary arteries and X-ray images are captured.
It tells us:
- Where the artery is narrowed
- How severe the narrowing appears
- The overall shape of the coronary artery
- How blood is flowing through the visible vessel
But angiography provides a two-dimensional silhouette of a three-dimensional artery.
It may not accurately reveal:
- The exact size of the artery
- The total plaque burden
- The composition and characteristics of plaque
- Calcium within the vessel wall
- Whether a stent is fully expanded
- Whether the stent is properly attached to the vessel wall
- Small dissections or other complications
This is where intravascular imaging changes the game.
IVUS: Ultrasound From Inside the Artery
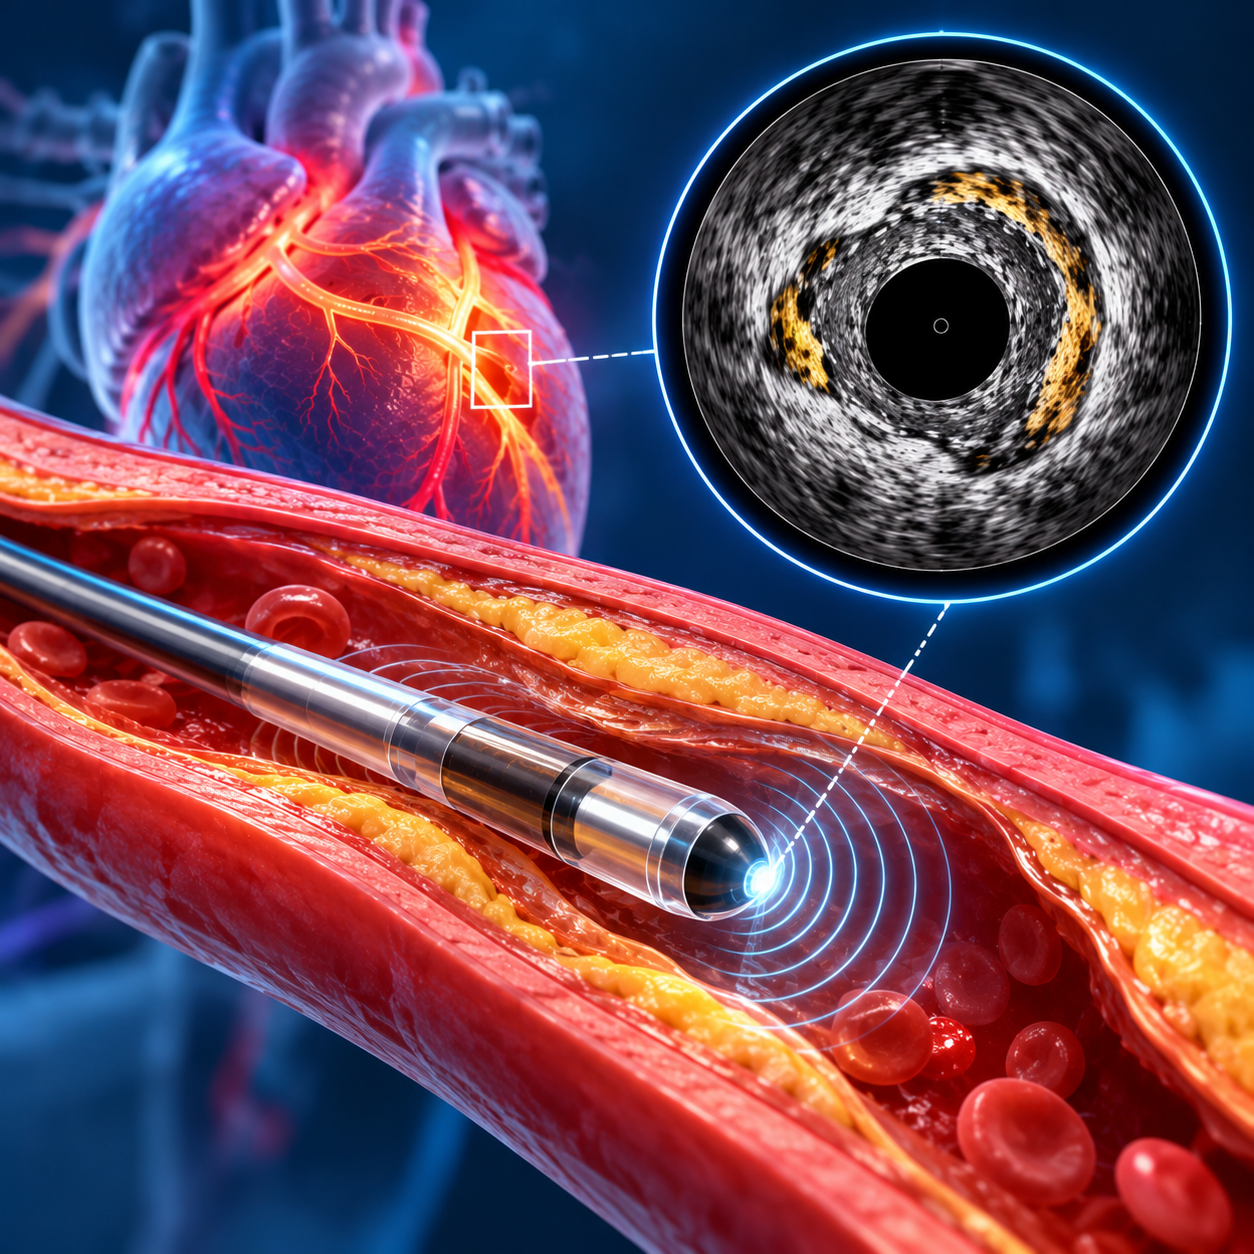
IVUS—Intravascular Ultrasound—uses a tiny ultrasound probe mounted on a catheter inside the coronary artery.
Instead of looking at the artery only from outside, the cardiologist can obtain cross-sectional images from within the vessel.
IVUS can help assess:
📏 Vessel Size
It helps determine the actual dimensions of the artery, helping the cardiologist select an appropriate stent size.
🧱 Plaque Burden
It can show how much plaque is present within the vessel.
🪨 Calcification
It can help identify and assess calcified lesions that may require careful preparation before stenting.
📐 Stent Expansion
After the stent is deployed, IVUS can help determine whether it has expanded adequately.
🔍 Stent Apposition
It can help identify areas where the stent may not be adequately opposed to the vessel wall.
This information can be particularly valuable in complex coronary interventions, including left-main disease, long lesions, bifurcations, heavily calcified arteries and other challenging anatomies.
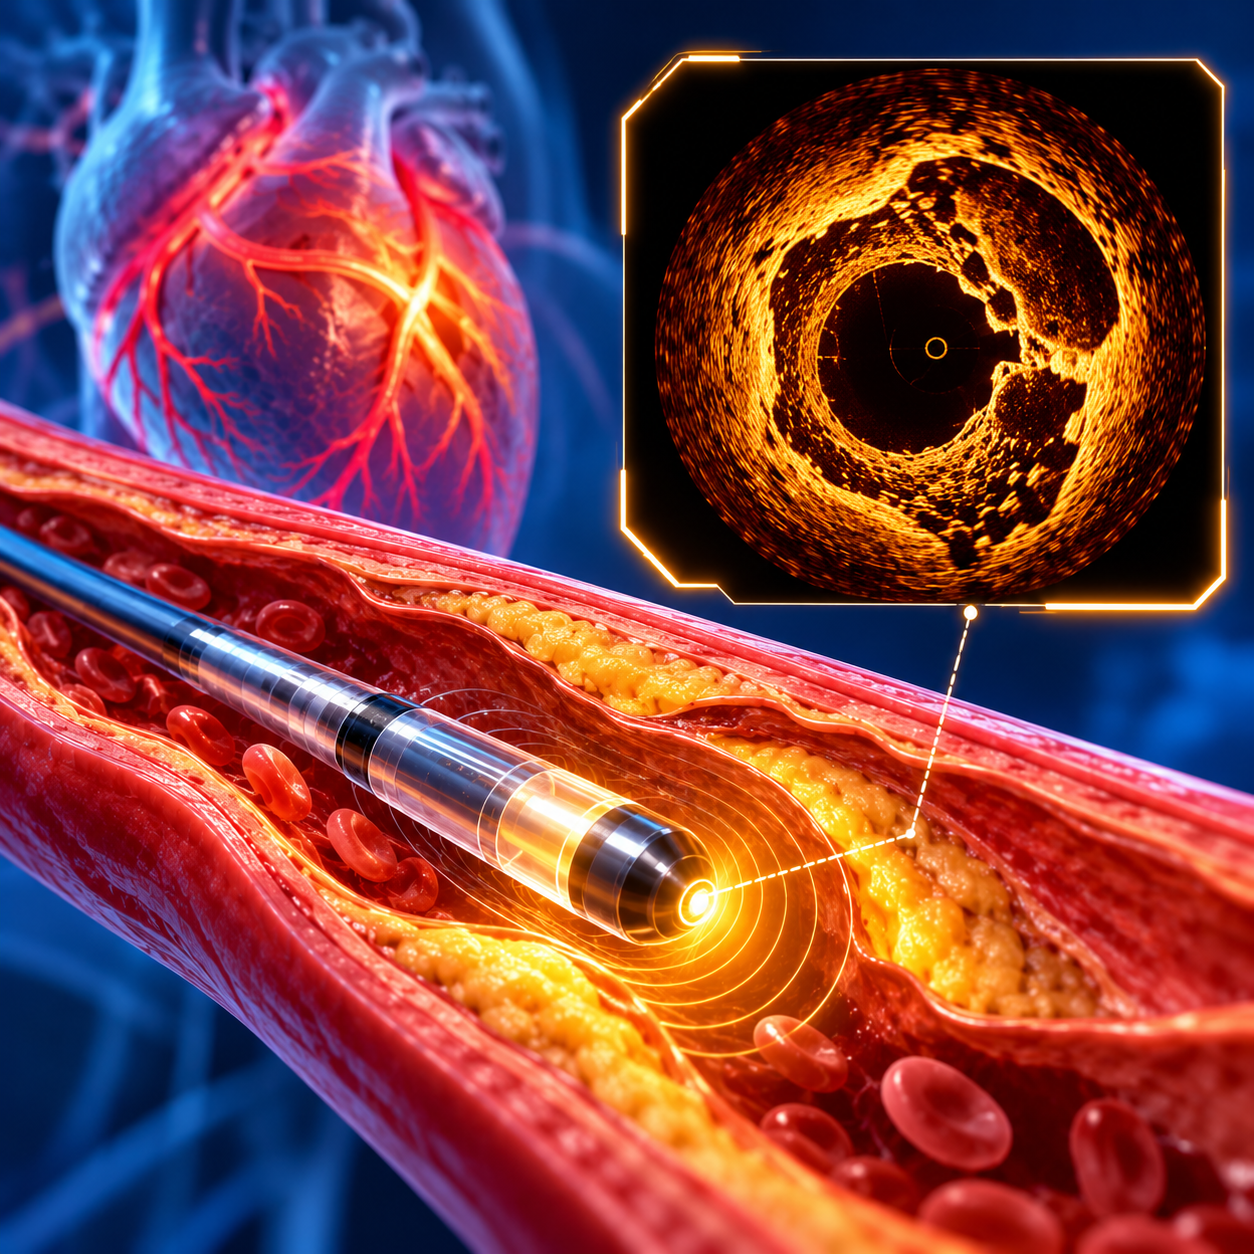
OCT: Seeing the Artery in Extraordinary Detail
If IVUS gives us a deeper ultrasound view, OCT provides extremely high-resolution optical imaging from inside the artery.
OCT uses near-infrared light to create detailed images of the vessel.
Its high resolution can help visualise:
- Fine details of coronary plaque
- Stent struts
- Stent expansion
- Stent apposition
- Small dissections
- Tissue characteristics around the stent
OCT generally provides higher spatial resolution than IVUS, although it requires adequate blood clearance and therefore has different practical considerations. Both technologies have important roles, and the choice depends on the clinical situation.
Where Does Artificial Intelligence Enter the Cath Lab?
Now comes the next revolution:
ARTIFICIAL INTELLIGENCE
AI is increasingly being explored across cardiovascular medicine—including imaging, lesion assessment, physiological assessment, procedural planning and decision support.
Imagine combining:
Human expertise + angiography + intravascular imaging + advanced computational analysis
This can potentially help the interventional cardiologist:
- Analyse complex coronary anatomy
- Identify and characterise lesions
- Perform automated measurements
- Assess vessel dimensions
- Support physiological assessment
- Assist procedural planning
- Improve workflow
- Reduce dependence on purely visual estimation
AI is NOT a replacement for the interventional cardiologist.
Rather, it can serve as an advanced technological assistant—helping the treating team process complex information and potentially make more precise decisions.
From “Look and Estimate” to “Measure and Optimise”
This is perhaps the biggest transformation in modern angioplasty.
Earlier approach:
Angiography → Visual assessment → Stent → Angiography again
Modern approach:
Angiography → Detailed lesion assessment → IVUS/OCT when appropriate → Precise sizing → Stent implantation → Intravascular optimisation → Final confirmation
This approach is especially valuable when coronary anatomy is complex.
And importantly, intravascular imaging isn’t about using technology simply because it exists.
The technology should answer a clinical question.
That is where the expertise of an experienced interventional cardiologist remains critical.
Why Stent Optimisation Matters?
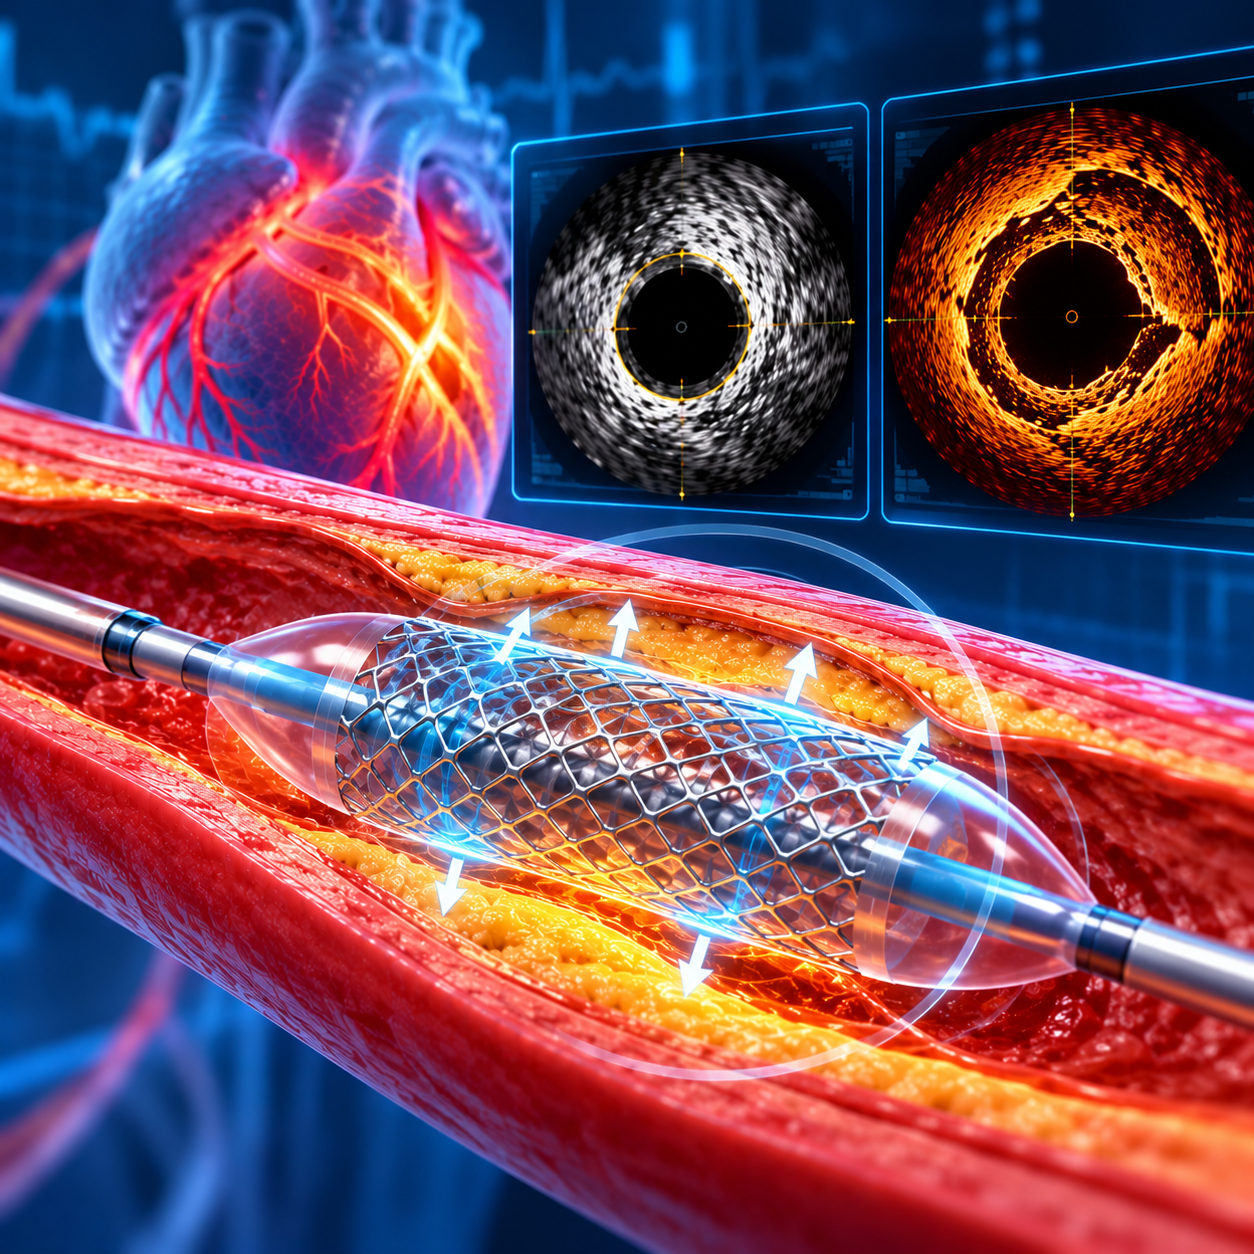
A stent that looks satisfactory on an angiogram may still have issues that are difficult to appreciate from angiography alone.
For example:
Under-expansion
The stent may not open sufficiently.
Malapposition
Some portions of the stent may not be adequately opposed to the vessel wall.
Edge problems
Disease or dissection may exist near the edge of the treated segment.
Geographical miss
The treated area may not completely cover the relevant diseased segment.
Intravascular imaging can identify problems that may otherwise be missed and allows the operator to correct them during the same procedure when appropriate.
Does Every Angioplasty Need IVUS or OCT?
Not necessarily.
The decision depends on the patient’s anatomy, lesion complexity, clinical circumstances, available technology and the treating cardiologist’s judgement.
However, intravascular imaging can be particularly useful in situations such as:
- Left main coronary artery disease
- Complex bifurcation lesions
- Heavily calcified arteries
- Long or diffuse lesions
- Uncertain vessel sizing
- Chronic total occlusions
- In-stent restenosis
- Stent thrombosis
- Unclear angiographic findings
- Complex/high-risk PCI
Current evidence continues to evolve, and recent trials have shown that the benefit of IVUS guidance can vary according to lesion type, procedural strategy and how imaging findings are acted upon.
So, advanced imaging is a tool—not a substitute for clinical judgement. \
MAHARASHTRA’S 1ST AI-POWERED CATHLAB WITH INBUILT CT SCAN at Jinkushal Cardiac Care Hospital
At Jinkushal Cardiac Care Hospital, we believe that patients deserve access to technology that represents the future of cardiovascular care.
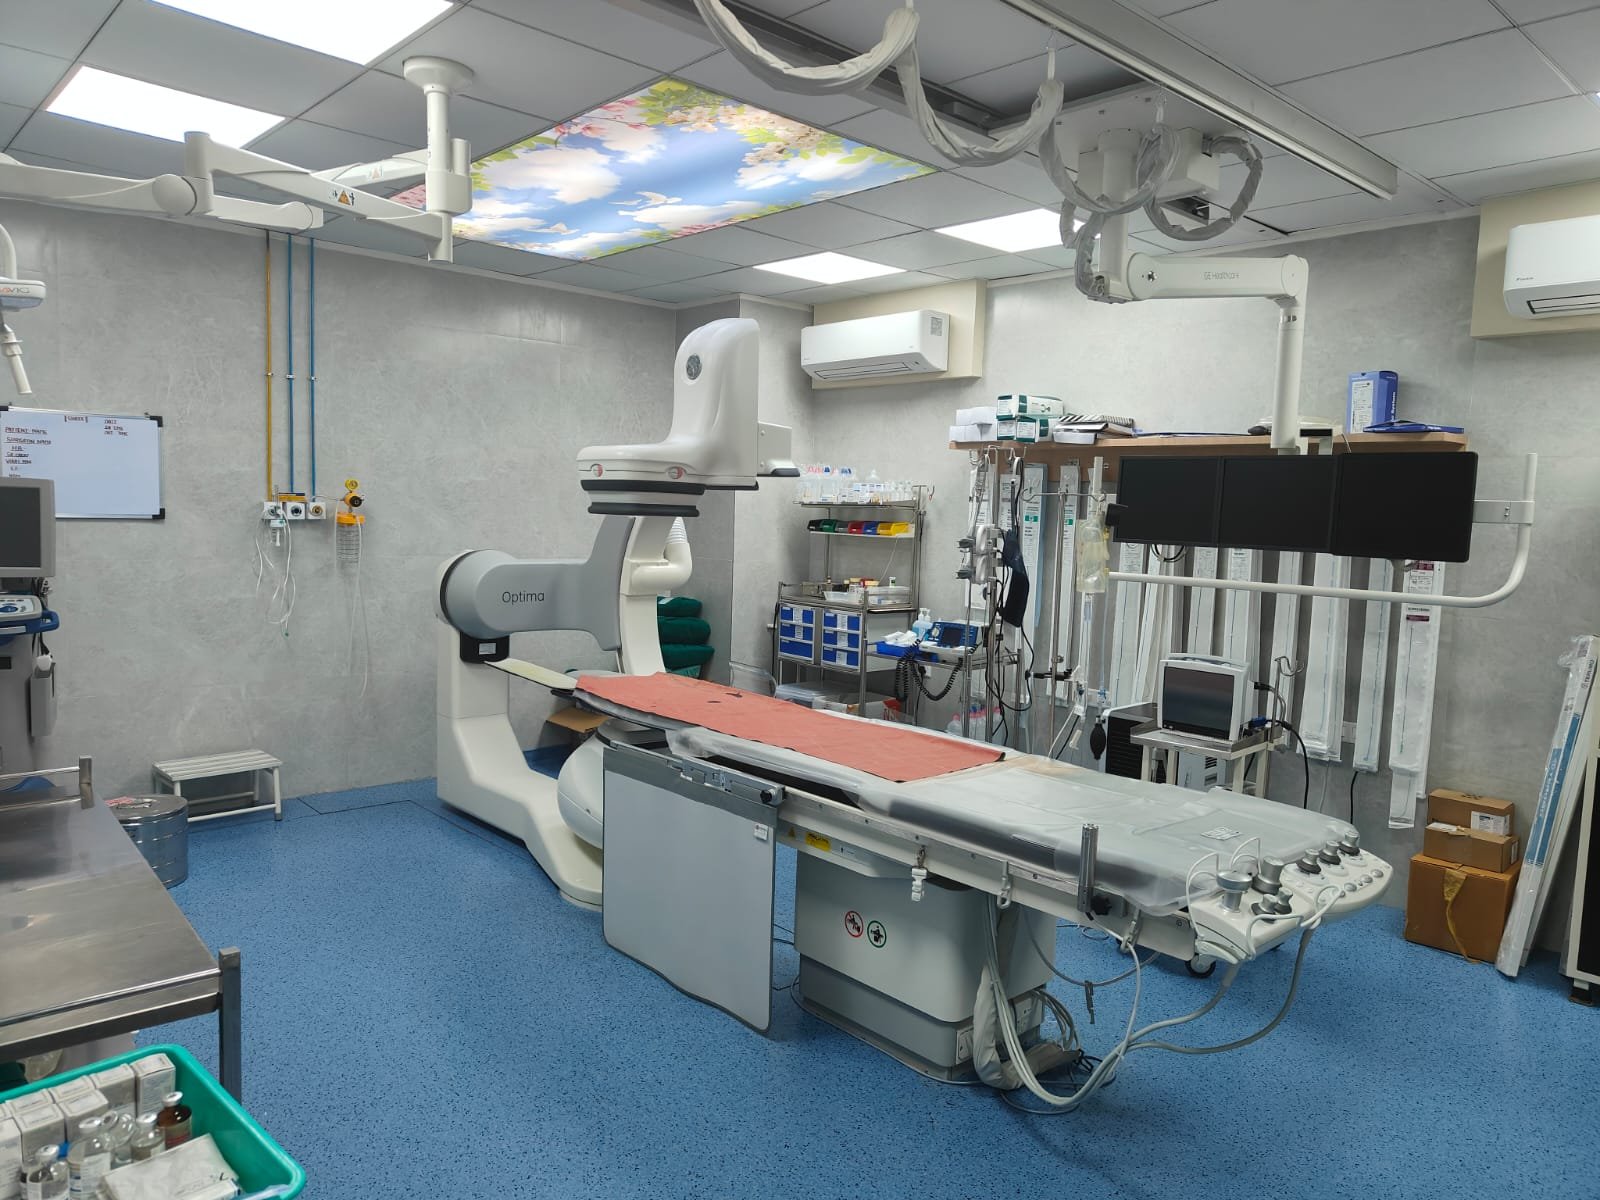
Jinkushal Cardiac Care Hospital is equipped with Maharashtra’s 1st AI Cathlab.
Our advanced cath lab combines modern interventional cardiology with evolving AI-enabled technologies, creating a platform designed to support more informed, precise and personalised coronary interventions.
For us, technology is not about having the newest machine.
It is about using the right technology for the right patient, at the right time.
Because behind every image, every measurement and every algorithm is one ultimate goal:
A safer, more precise and better-informed heart procedure for the patient.
When your heart needs an intervention, ask not only:
“Can the blockage be treated?”
but also:
“How precisely can it be treated?”
This Blog is intended for general awareness and does not replace individual medical advice. The use of IVUS, OCT, AI-enabled technologies or other advanced techniques is determined by the treating interventional cardiologist based on the patient’s clinical condition and coronary anatomy.